Personalized Medical Care & Dedicated International Patient Concierge

Specialty Overview
Endovenous Vein Ablation
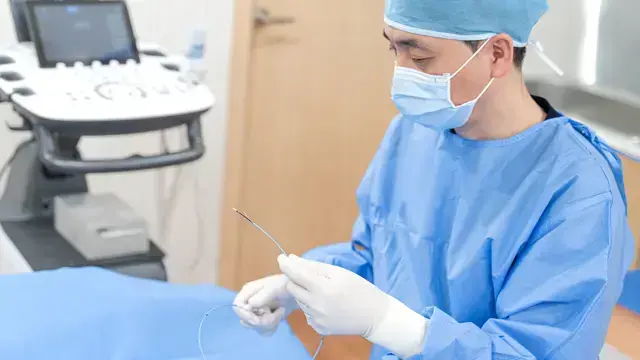
Endovenous vein ablation is the closure of a refluxing vein — most often the great or small saphenous vein — from within the vein itself, using a catheter placed under ultrasound guidance instead of surgical removal.
Schedule a ConsultationEndovenous Vein Ablation
Medically reviewed by Dr. Dong-Hyuk Kim, Board-Certified General Surgeon, Medical DirectorIum Hazi Varicose Vein Clinic, Seocho-gu, Seoul
Endovenous vein ablation is a minimally invasive treatment that closes a faulty vein from the inside rather than removing it. A catheter or similar device is passed into the vein through a small access point under ultrasound guidance, and thermal energy, a medical adhesive or another ablation method seals the vein along its length. Blood is then carried by healthier veins, and the treated vein is gradually absorbed.
What Is Endovenous Vein Ablation?
Endovenous vein ablation is the closure of a refluxing vein — most often the great or small saphenous vein — from within the vein itself, using a catheter placed under ultrasound guidance instead of surgical removal.
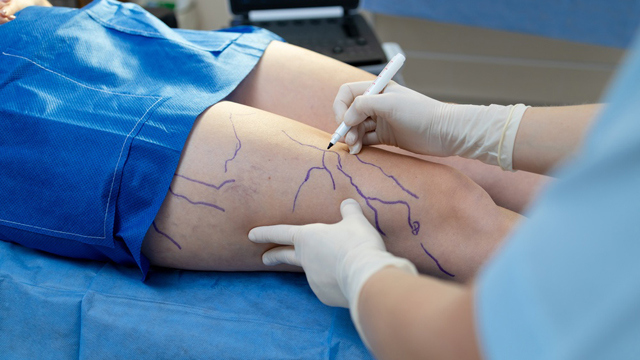
The target is the vein that is leaking, not the visible vein on the surface; which one that is comes from the ultrasound assessment.
Access is through a small point in the skin rather than a surgical incision along the leg.
The vein is closed by energy, adhesive or a mechanochemical method, depending on the technique chosen.
It is commonly performed as an outpatient procedure, and many patients walk shortly afterwards.
It is generally less invasive than traditional vein stripping.
The underlying problem it addresses is valve failure. When the one-way valves inside a leg vein stop closing, blood flows backwards and pools, which is how MedlinePlus, from the US National Library of Medicine, describes the formation of varicose veins in general. Closing the leaking channel removes the route that the backward flow takes. In national guidance for the treatment category, endothermal ablation — radiofrequency or laser — is described by the UK National Health Service as the usual first-choice specialist treatment, performed under local anaesthetic via a catheter placed under ultrasound guidance as a same-day procedure, and the National Institute for Health and Care Excellence sets out the order in which endothermal ablation, foam sclerotherapy, surgery and compression hosiery are considered for confirmed truncal reflux.
Who Performs Endovenous Vein Ablation at Ium Hazi Varicose Vein Clinic

Dr. Dong-Hyuk Kim
Board-certified general surgeon
Dr. Dong-Hyuk Kim is a board-certified general surgeon and the Medical Director of Ium Hazi Varicose Vein Clinic. He completed his medical education at Sungkyunkwan University School of Medicine and serves as Executive Director of the Korean Society of Phlebology.
Ium Hazi Varicose Vein Clinic operates a single-director system: Dr. Dong-Hyuk Kim personally performs every consultation, diagnostic ultrasound, procedure and post-operative follow-up, and the clinic deliberately limits its schedule to one or two surgical cases per day.
Dr. Kim's documented core specializations include 4th-generation 1940 nm endovenous laser surgery and radiofrequency ablation, alongside vascular ultrasound diagnosis; his documented subspecialty technique expertise covers VenaSeal vein closure and mechanochemical ablation. He is a founding member of the Venous Disease Research Society and holds an adjunct professorship at Samsung Medical Center, Sungkyunkwan University School of Medicine. His presentations include work on laser surgery for varicose veins at the UIP World Congress of Phlebology in Boston in 2013, and he is a co-translator of professional texts on ambulatory phlebectomy and on current varicose vein techniques.
This page does not cite case counts, awards, ratings or patient testimonials. Where the clinic publishes such figures they are self-reported and unaudited, and they do not describe what any individual patient should expect.
Endovenous Vein Ablation Options and Types Available
Ablation is a family of techniques rather than one procedure. The clinic documents four, split between thermal methods, which close the vein with heat, and non-thermal methods, which close it without.
Method | How the vein is closed | Group |
|---|---|---|
Laser energy delivered along the inside of the vein; the clinic uses a 4th-generation 1940 nm system | Thermal | |
Radiofrequency energy delivered through a catheter; the clinic uses a Medtronic ClosureRFG and RFG 3D system | Thermal | |
A medical adhesive seals the vein, which then closes by adhesion and fibrosis | Non-thermal | |
A rotating wire combined with a chemical agent closes the vein | Non-thermal |
The clinic's stated basis for choosing between them is the affected vein, the ultrasound findings, the vein anatomy, the symptoms and patient-specific factors — not a house preference. The practical difference between the two groups is how anaesthesia is handled: thermal techniques require tumescent local anaesthesia placed around the vein to protect surrounding tissue from the heat, while NICE's account of cyanoacrylate glue occlusion describes the adhesive technique as delivered under ultrasound guidance without tumescent anaesthesia and with a reduced need for compression afterwards. NICE also recognises mechanochemical ablation as a non-thermal technique that closes the vein using a rotating wire together with a chemical agent. Catheter-based ablation as a category is typically applied to the great, small and accessory saphenous veins, because a catheter cannot easily negotiate a tortuous surface vein, as RadiologyInfo.org from the Radiological Society of North America and the American College of Radiology explains.
Regulatory approval, clearance or certification status for the devices used at this clinic is not documented in the clinic's source material, so no approval, clearance or certification claim is made on this page.
Who Is a Good Candidate for Endovenous Vein Ablation?

Adults with confirmed venous reflux identified through clinical assessment and vascular ultrasound.
Adults with another treatable vein problem where the affected vein is suitable for an endovenous approach.
Patients with symptomatic varicose veins — aching, heaviness, swelling — arising from reflux in a treatable vein.
Patients who want to treat symptomatic or visible varicose veins while avoiding traditional surgical vein stripping.
Suitability depends on the affected vein, the anatomy, the symptoms, the medical history and the treatment goals, and it is settled after examination and ultrasound rather than in advance.
The clinic also documents who may not be suitable:
People with certain vascular conditions.
People with an active infection at the treatment site.
People whose vein anatomy is unsuitable for a catheter-based approach.
People with severe peripheral arterial disease.
People with certain blood-clotting conditions or severe circulation problems, and people with other medical conditions that make treatment inadvisable at that time.
Final suitability is determined by a vascular specialist after examination and ultrasound evaluation. Nothing in either list is a self-assessment tool.
What to Expect: Procedure, Recovery, and Results Timeline
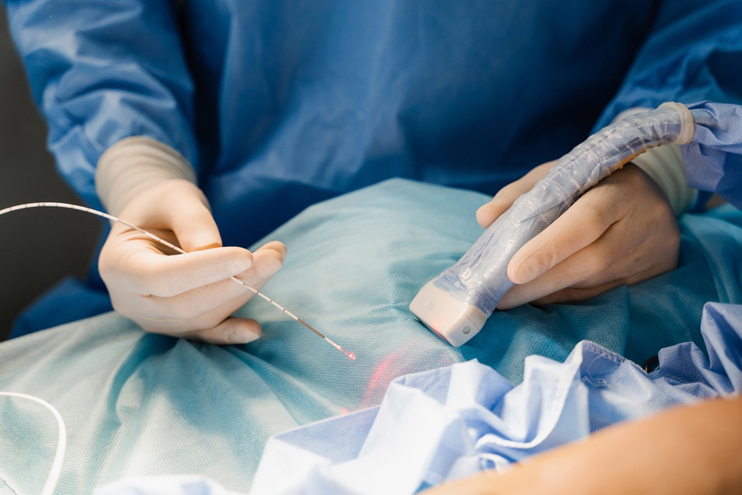
The clinic documents the sequence as: vascular ultrasound mapping of the affected vein; preparation and local anaesthesia; a small access point made in the skin; the catheter or treatment device inserted into the vein under ultrasound guidance; energy, adhesive or another ablation method used to close the target vein; the device removed and the access site dressed; and post-procedure assessment and walking before discharge when appropriate.
Stage | What happens | Timing |
|---|---|---|
Before treatment | Full medical history and medication list, including blood thinners and supplements; the clinic's instructions on medication, eating and drinking, and skin preparation | At and before the pre-treatment visit |
Anaesthesia | Local anaesthesia; tumescent anaesthesia may be used for thermal ablation; additional sedation considered case by case | On the day |
Treatment | Catheter placed and the vein closed under ultrasound guidance | Commonly about 30–60 minutes, depending on the number and location of veins |
Immediately after | Assessment and walking before discharge when appropriate | Same day |
First weeks | Bruising, tenderness or tightness may continue | Several days to a few weeks |
Follow-up | Activity, compression if prescribed, and follow-up examinations including ultrasound to assess the result | Per the individual plan |
Local anaesthesia means the procedure is generally associated with minimal discomfort, with mild soreness, tightness or bruising afterwards. Many patients can walk shortly after treatment and return to routine light activities relatively quickly. Recovery varies with the technique used, the number of veins treated and individual response.
Results do not all arrive at once. The treated vein is intended to remain closed, while symptoms and appearance improve progressively as the body adapts and absorbs the vein; follow-up ultrasound may be used to confirm closure. Veins that were not treated can develop problems later, so long-term results vary. This clinic does not publish closure rates, success rates or recurrence rates, so none are stated here. Figures published for a treatment category as a whole do not describe the results of any individual clinic or patient.
For patients travelling from the United States, the required stay depends on the treatment selected, the recovery and the recommended follow-up, and the clinic asks international patients to confirm the itinerary before booking return travel. Air travel should be planned only after the treating physician confirms it is appropriate; the timing depends on the extent of treatment, recovery and individual risk factors including clotting risk. That caution is not specific to this clinic — the US Centers for Disease Control and Prevention notes that travel over four hours raises clot risk through immobility, and lists recent surgery among the contributing factors.
Combining Endovenous Vein Ablation with Other Treatments
Closing a refluxing trunk does not always deal with every vein a patient can see. The clinic documents that endovenous ablation may be combined with other vein treatments, such as ambulatory phlebectomy, when additional visible or symptomatic veins require treatment, and that the combination is determined by the treating physician.
Micro-Phlebectomy — targeted removal of surface varicose veins through micro-incisions, used alongside ablation when surface veins remain.
Diagnosis & Evaluation — the vascular ultrasound assessment that decides what is treated and in what order, and provides the baseline for comparison afterwards.
Post-treatment vascular ultrasound examinations, which the clinic includes in its aftercare.
General alternatives to ablation include compression therapy, ambulatory phlebectomy and traditional surgical vein treatment. Which is appropriate depends on the vein involved, the severity of the venous disease, the symptoms, the anatomy and the ultrasound findings.
Safety, Precision, and Clinic Standards
The risks below are the ones this clinic documents in its own treatment information. No procedure is free of risk, and a written list is not a substitute for the discussion of risks and alternatives that takes place during consultation.
Common and usually temporary effects include bruising, swelling, tenderness, tightness, mild pain, temporary numbness, skin irritation, skin discolouration, or discomfort along the treated vein.
Less common complications documented by the clinic include infection, bleeding, nerve irritation or numbness, blood clots, skin injury, vein inflammation, allergic reactions to adhesive or sclerosant materials, incomplete closure, reopening of the treated vein, and — rarely — more serious complications. Effects vary by technique.
Thrombotic complications are the category risk that most warrants naming rather than summarising. The Society for Vascular Surgery describes endovenous thermal ablation as carrying a low but definite category-level risk of endovenous heat-induced thrombosis, superficial venous thrombosis and deep vein thrombosis, with major deep vein thrombosis and pulmonary embolism extremely rare, and notes that heat-induced thrombosis may require a period of anticoagulation and follow-up imaging. RadiologyInfo's account of the same category lists bruising, tenderness, thrombophlebitis, rare thermal nerve injury and very rare pulmonary embolism. European guidance on chronic venous disease of the lower limbs covers both thermal and non-thermal ablation of incompetent saphenous trunks in adults.
The clinic's documented risk-reduction process is vascular assessment and ultrasound evaluation of the veins, patient selection, image guidance during treatment, and post-procedure monitoring and follow-up. The clinic's stated quality process is doctor-led diagnosis, consultation, surgery and post-operative care; pre-operative vascular ultrasound and clinical evaluation; a deliberately limited daily surgical caseload; strict sterilisation using autoclave and ethylene oxide gas systems; no reuse of single-use devices; and post-operative vascular ultrasound monitoring and follow-up care.
The clinic's documented equipment includes a Samsung Medison V8 high-resolution vascular ultrasound system, a VeinViewer Flex vein visualisation device, a 4th-generation 1940 nm endovenous laser system and a Medtronic ClosureRFG and RFG 3D radiofrequency system. Instruments are sterilised by autoclave and ethylene oxide gas, and single-use devices are not reused.
The clinic is a Registered Medical Institution for Attracting Foreign Patients, certified by the Republic of Korea's Ministry of Health and Welfare under the Medical Overseas Expansion and Foreign Patients Attraction Act.
This page does not quote prices and does not describe insurance coverage. Fees, what a quotation includes, and any question of reimbursement are discussed during consultation, and patients outside Korea should confirm coverage with their own insurer.
The Bottom Line
Endovenous ablation closes a leaking vein from the inside through a small access point, under ultrasound guidance, instead of removing it surgically.
Four methods are available at this clinic — laser, radiofrequency, adhesive and mechanochemical — and the choice follows the ultrasound findings and the anatomy.
It is commonly an outpatient procedure under local anaesthesia, with walking soon afterwards and bruising or tightness for several days to a few weeks.
Documented risks run from bruising and temporary numbness to infection, nerve irritation, clotting complications and incomplete closure.
Untreated veins can develop problems later, so follow-up, including ultrasound, is part of the treatment rather than an optional extra.
Frequently Asked Questions
How is the vein I can see related to the vein that gets treated?
Often not directly. The bulging vein on the surface is usually downstream of a leaking trunk vein deeper in the leg, most often the great or small saphenous vein, and that trunk is what the catheter treats. This is why the ultrasound assessment comes first: it establishes which vein is the source. If prominent surface veins remain afterwards, they are addressed separately.
Which ablation method will I have?
That is decided from your ultrasound findings, your vein anatomy, your symptoms and your medical history, not chosen from a menu in advance. The clinic offers thermal methods using laser or radiofrequency energy and non-thermal methods using adhesive or a mechanochemical technique. The most practical difference for a patient is that thermal methods use tumescent anaesthesia around the vein and non-thermal methods generally do not.
Will I be asleep?
Local anaesthesia is what is commonly used, including tumescent anaesthesia around the target vein for thermal ablation. Additional sedation may be considered depending on the procedure and individual circumstances, and the anaesthesia plan is set by the physician.
How long does the procedure take?
Generally about 30 to 60 minutes as an outpatient treatment, depending on how many veins are treated and where they are. The number of visits, including follow-up, depends on your condition and plan.
When can I fly back to the United States?
Only after the treating physician confirms it is appropriate. The timing depends on how much was treated, how your recovery is going, and your individual risk factors for complications such as blood clots. Long-haul travel is itself a recognised clot risk factor, which is why this is a decision made with the doctor rather than a fixed number of days.
What should I avoid afterwards?
Follow the physician's instructions on strenuous exercise, prolonged sitting or standing, bathing, compression garments if prescribed, and travel, and attend the recommended follow-up examinations. Before treatment, avoid any activity or medication the physician specifically restricts, and disclose all medications including blood thinners and supplements.
Can ablation be used if varicose veins came back after a previous treatment?
Whether it can depends on what the ultrasound shows now — which vein is refluxing, what was treated before, and whether the current anatomy suits a catheter-based approach. That reassessment is the starting point, and the answer comes from it rather than from the history alone.
What is tumescent anaesthesia, and why does a thermal method need it?
Tumescent anaesthesia is a dilute local anaesthetic placed in the tissue around the target vein rather than into it. For the treatment category as a whole, RadiologyInfo describes it as part of how catheter-based thermal ablation is performed: it numbs the area and also separates the vein from the surrounding tissue so that heat delivered inside the vein stays there. Non-thermal methods, which close the vein with adhesive or a mechanochemical technique, generally do not require it, and that is one of the practical differences between the two groups.
Book a Consultation at Ium Hazi Varicose Vein Clinic
If you are considering endovenous vein ablation in Seoul, the first step is the assessment that establishes which vein is leaking and which technique suits it.
To arrange a consultation, use the clinic's contact page at contact us or call . English-language support is available for international patients.
Ium Hazi Varicose Vein Clinic is on the 2nd floor of K-Tower, 320 Seocho-daero, Seocho-gu, Seoul 06633, Republic of Korea. More about the clinic is on its About Us page.
Disclaimer
Individual results may vary. All surgical and non-surgical procedures have potential risks and limitations. Your suitability for treatment, expected results, costs, and recovery time will be discussed with Dr. Dong-Hyuk Kim during your personal consultation. The information provided is for general educational purposes and does not guarantee a specific treatment outcome.
Sources & Further Reading
Quality statement 3: Treatment of varicose veins (QS67) — NICE
Endovenous mechanochemical ablation for varicose veins (HTG414) — NICE
Cyanoacrylate glue occlusion for varicose veins (IPG670) — NICE
Endovenous thermal ablation and thrombotic complications — Society for Vascular Surgery
Varicose Veins — MedlinePlus, US National Library of Medicine
Understanding Your Risk for Blood Clots with Travel — Centers for Disease Control and Prevention
Related Services
Procedures available within our clinical departments.
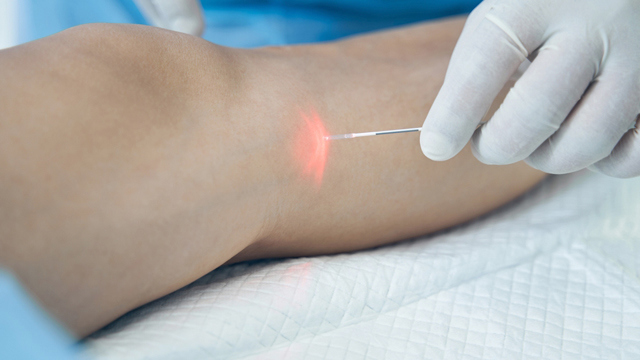
Endovenous Laser Ablation
Endovenous laser ablation is the closure of an abnormal vein from the inside using laser energy delivered along a fibre placed under ultrasound guidance, used for appropriately diagnosed venous reflux and the varicose vein symptoms that follow from it.
Learn More
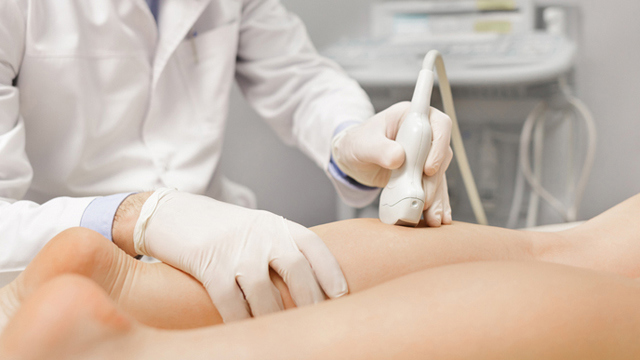
Vascular Ultrasound Examination
A vascular ultrasound examination evaluates the condition of the leg veins — deep, saphenous, subcutaneous and perforating — assessing their size, shape, location and blood-flow patterns, and showing reflux in real time.
Learn More
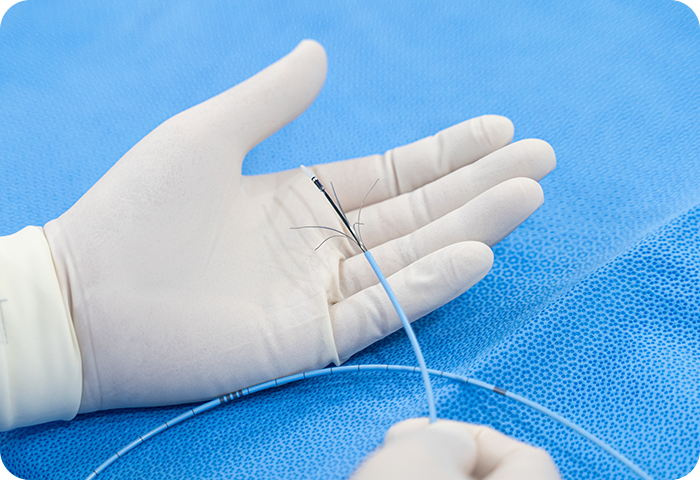
Mechanochemical Ablation
Mechanochemical ablation closes a refluxing vein by combining two actions in one catheter pass: mechanical irritation of the inner vein wall and delivery of a chemical sclerosing agent, without heat.
Learn More