Personalized Medical Care & Dedicated International Patient Concierge

Endovenous Vein Ablation · Needs Clinic Confirmation
Mechanochemical Ablation
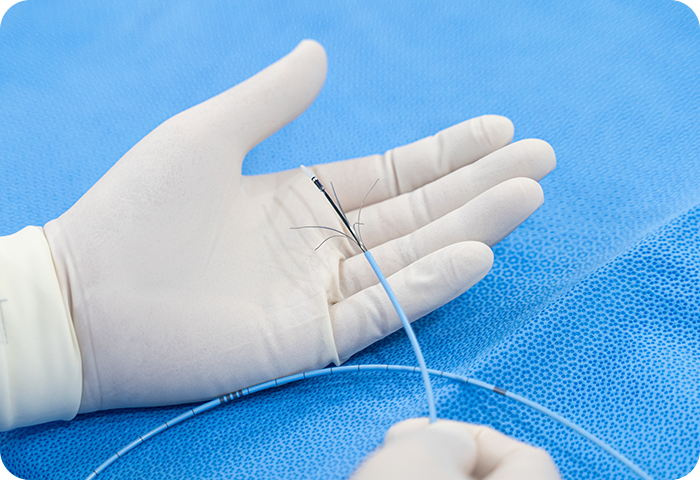
Mechanochemical ablation closes a refluxing vein by combining two actions in one catheter pass: mechanical irritation of the inner vein wall and delivery of a chemical sclerosing agent, without heat.
Schedule a ConsultationMechanochemical Ablation
Medically reviewed by Dr. Dong-Hyuk Kim, Board-Certified General Surgeon, Medical DirectorIum Hazi Varicose Vein Clinic, Seocho-gu, Seoul
Mechanochemical ablation is a minimally invasive vein treatment that uses a catheter to mechanically disrupt the vein wall while delivering a sclerosing agent, so that the treated vein closes without thermal energy. It is one of the non-thermal options for venous reflux at Ium Hazi Varicose Vein Clinic, chosen on the ultrasound findings rather than offered as a default.
What Is Mechanochemical Ablation?
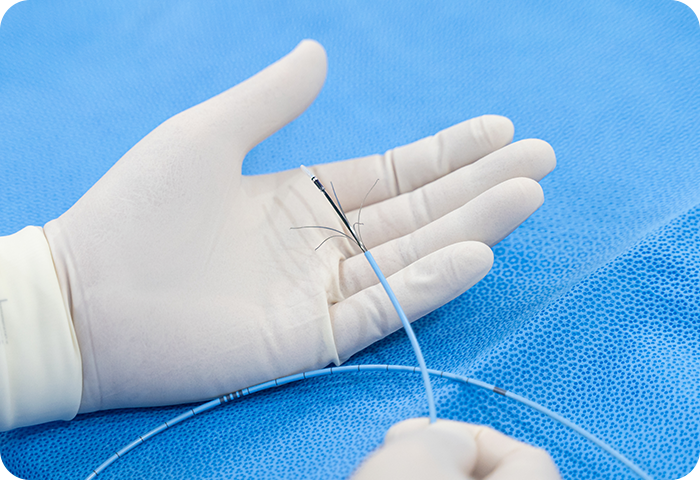
Mechanochemical ablation closes a refluxing vein by combining two actions in one catheter pass: mechanical irritation of the inner vein wall and delivery of a chemical sclerosing agent, without heat.
A catheter is placed in the affected vein under ultrasound guidance through a small access point.
The catheter mechanically disrupts the inner vein wall while the sclerosing agent is delivered.
The treated vein closes and blood is redirected through healthier veins.
No thermal energy is applied, so the vein is not heated and is not physically removed.
The specific catheter, sclerosant, dosage and technique depend on the treated vein and the physician's protocol.
The technique is recognised in national guidance for this treatment category. The National Institute for Health and Care Excellence describes endovenous mechanochemical ablation as a non-thermal technique that closes the vein using a rotating wire combined with a chemical agent, and its account of the wider set of interventional options lists mechanochemical ablation alongside endothermal ablation, foam sclerotherapy and surgery.
This page makes no claim about how well this method works. The clinic has not confirmed approved effectiveness claims for mechanochemical ablation, so none are stated here — what follows describes what the treatment is, who it may suit, what happens, and what can go wrong. Where a comparison between methods matters to your decision, that comparison belongs in the consultation, where it can be made against your own ultrasound findings.
Regulatory approval, clearance or certification status for the devices used at this clinic is not documented in the clinic's source material, so no approval, clearance or certification claim is made on this page.
Who Performs Mechanochemical Ablation at Ium Hazi Varicose Vein Clinic

Dr. Dong-Hyuk Kim
Board-certified general surgeon
Dr. Dong-Hyuk Kim is a board-certified general surgeon and the Medical Director of Ium Hazi Varicose Vein Clinic. He completed his medical education at Sungkyunkwan University School of Medicine and serves as Executive Director of the Korean Society of Phlebology.
Ium Hazi Varicose Vein Clinic operates a single-director system: Dr. Dong-Hyuk Kim personally performs every consultation, diagnostic ultrasound, procedure and post-operative follow-up, and the clinic deliberately limits its schedule to one or two surgical cases per day.
Mechanochemical ablation is one of Dr. Kim's documented subspecialty techniques, alongside VenaSeal vein closure — the clinic's two non-thermal options, held alongside the laser and radiofrequency methods listed among his core specializations. The practical significance is that a non-thermal technique is available when the assessment points to one, rather than the assessment being shaped by which single technique the clinic performs.
This page does not cite case counts, awards, ratings or patient testimonials. Where the clinic publishes such figures they are self-reported and unaudited, and they do not describe what any individual patient should expect.
Who Is a Good Candidate for Mechanochemical Ablation?
Patients with confirmed venous reflux whose vein anatomy is suitable for mechanochemical treatment.
Patients with symptomatic varicose veins whose affected vein is assessed as suitable on clinical examination and vascular ultrasound.
Patients considering a non-thermal alternative to thermal vein ablation methods such as laser or radiofrequency ablation.
Suitability is determined by a vascular specialist and ultrasound assessment.
The clinic documents who may not be suitable:
Patients with an allergy or contraindication to the sclerosing agent.
Patients with an infection at the treatment site.
Patients whose vein anatomy is unsuitable.
Patients with other medical conditions that make the procedure inappropriate.
Sensitivity to the sclerosing agent is the exclusion specific to this technique, which is why the allergy and medication review before treatment is a clinical step rather than paperwork. Final suitability requires physician assessment and ultrasound evaluation.
What to Expect: Procedure, Recovery, and Results Timeline
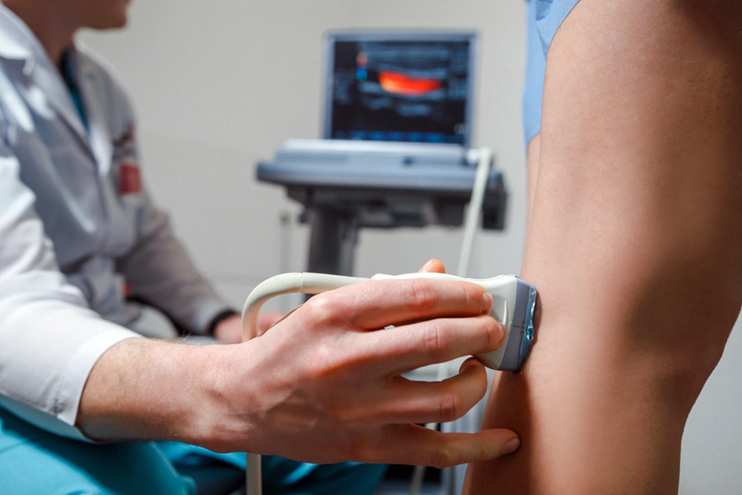
The clinic sets the steps out in this order: the target vein is mapped on ultrasound; local anaesthesia is given at the catheter entry site; a catheter is inserted into the affected vein under ultrasound guidance; the catheter mechanically disrupts the inner vein wall while the sclerosing agent is delivered; the treated vein closes so that blood redirects through healthier veins; and the patient is assessed before discharge.
Stage | What happens | Timing |
|---|---|---|
Before treatment | Complete medical history, allergies and medication list including blood thinners and supplements; clinic instructions on medication, fasting if sedation is planned, activity and transport | Before the day |
Anaesthesia | Local anaesthesia at the catheter entry site; sedation considered depending on the patient and clinic protocol | On the day |
Treatment | Catheter placed under ultrasound guidance; mechanical disruption and sclerosant delivered together | About 30 minutes to 1 hour, depending on the number and location of veins |
Discharge | Assessment before discharge; many patients leave the same day | Same day |
Early recovery | Temporary bruising, swelling, tenderness or tightness may occur; activity resumed gradually | First days to weeks |
Follow-up | Clinical assessment and vascular ultrasound where indicated, to evaluate closure | Per the plan |
Because local anaesthesia is used only at the catheter entry site rather than around the whole vein, the anaesthesia step is smaller than for a heat-based method — one of the practical differences between thermal and non-thermal techniques. Patients may still experience temporary soreness, tenderness, tightness or bruising after treatment, and pain levels vary between individuals.
Aftercare follows the physician's instructions on walking and activity, wound care, medication, and compression where prescribed, with strenuous activity, smoking and alcohol avoided when advised during the initial recovery period, and recommended follow-up appointments attended.
The treated vein closes progressively after the procedure rather than at once, with follow-up clinical assessment or ultrasound used to evaluate closure. Symptoms can improve over time, and new or recurrent venous problems may still develop later. This clinic does not publish closure rates, success rates or recurrence rates, so none are stated here. Figures published for a treatment category as a whole do not describe the results of any individual clinic or patient.
For patients travelling from the United States, the clinic documents no universal stay requirement: allow time for the initial consultation, the ultrasound assessment, the procedure and any recommended follow-up, and confirm the schedule with the clinic. Return-flight timing depends on recovery, the extent of treatment and the physician's assessment, and should be confirmed with the physician rather than fixed to a number of days in advance. The Centers for Disease Control and Prevention notes for travellers generally that journeys over four hours raise clot risk through immobility, and lists recent surgery and varicose veins among the contributing factors.
Combining Mechanochemical Ablation with Other Treatments
The clinic documents that mechanochemical ablation may be combined with procedures such as phlebectomy when clinically appropriate — the usual reason being that closing a trunk vein does not remove prominent surface veins that are already there.
Micro-Phlebectomy — the procedure the clinic names specifically as a possible pairing with this one, for surface veins the catheter does not reach.
Vascular Ultrasound Examination — the mapping step that opens this procedure and the check that closes it.
Endovenous Vein Ablation — the family of closure techniques of which this is the second non-thermal option.
The alternatives the clinic lists for the same vein condition are endovenous laser ablation, radiofrequency ablation, cyanoacrylate adhesive closure such as VenaSeal, phlebectomy and traditional vein surgery.
Safety, Precision, and Clinic Standards

The risks below are the ones this clinic documents in its own treatment information. No procedure is free of risk, and a written list is not a substitute for the discussion of risks and alternatives that takes place during consultation.
Common and usually temporary effects include bruising, swelling, tenderness, tightness or temporary discomfort along the treated vein.
Documented complications include inflammation of the treated vein, allergic reaction to the sclerosing agent, nerve irritation, infection, blood clots, skin changes, and incomplete or recurrent vein closure.
The reaction to the sclerosing agent is the risk that belongs to this method specifically. Thermal techniques carry burn and heat-related nerve injury risks that this one does not; in exchange, a chemical agent is introduced into the vein, and the body can react to it. Neither set of risks is the smaller one in general — they are different, and which matters more depends on the patient.
The clinic's documented risk-reduction measures for this treatment are appropriate patient selection, medical-history review, vascular ultrasound assessment, ultrasound guidance during treatment, appropriate selection of the sclerosing agent, and follow-up assessment when indicated. The clinic's stated quality process is doctor-led diagnosis, consultation, surgery and post-operative care; pre-operative vascular ultrasound and clinical evaluation; a deliberately limited daily surgical caseload; strict sterilisation using autoclave and ethylene oxide gas systems; no reuse of single-use devices; and post-operative vascular ultrasound monitoring and follow-up care.
The clinic is a Registered Medical Institution for Attracting Foreign Patients, certified by the Republic of Korea's Ministry of Health and Welfare under the Medical Overseas Expansion and Foreign Patients Attraction Act.
This page does not quote prices and does not describe insurance coverage. Fees, what a quotation includes, and any question of reimbursement are discussed during consultation, and patients outside Korea should confirm coverage with their own insurer.
The Bottom Line
The catheter does two things at once: it mechanically disrupts the inner vein wall and delivers a sclerosing agent, closing the vein without heat.
Local anaesthesia is used at the catheter entry site, and the procedure commonly takes about 30 minutes to 1 hour with same-day discharge possible.
Allergy or contraindication to the sclerosing agent is the exclusion specific to this technique.
Documented risks include vein inflammation, reaction to the sclerosant, nerve irritation, infection, blood clots, skin changes and incomplete or recurrent closure.
No effectiveness claim is made for this method on this page, because the clinic has not confirmed one.
Frequently Asked Questions
How does it close the vein without heat?
Two actions combine. The catheter mechanically irritates the inner lining of the vein, and a sclerosing agent is delivered at the same time. The mechanical disruption is what lets the chemical act on the vein wall effectively, and the vein then closes progressively rather than instantly. No heat is applied at any stage.
What anaesthesia will I need?
Local anaesthesia at the catheter entry site is what is commonly used, with sedation considered depending on you, the extent of treatment and clinic protocol. That is a smaller anaesthesia step than a heat-based method requires, because there is no surrounding tissue to protect from heat.
How long does it take, and will I stay overnight?
The procedure commonly takes about 30 minutes to 1 hour, depending on how many veins are treated and where they are, and it is generally an outpatient procedure with same-day discharge possible. You are assessed before you leave.
What should I tell the clinic beforehand?
A complete medical history, all your allergies, and every current medication including blood thinners and supplements. Allergies matter more here than they would for a purely mechanical or thermal technique, because a chemical agent is part of the treatment.
Is this better than laser or radiofrequency?
This page does not answer that, and deliberately so: the clinic has not confirmed comparative effectiveness claims for this method, and a page that supplied one anyway would be inventing it. What can be said is that the mechanisms differ, the exclusions differ, and the choice is made at consultation from the ultrasound findings and your own circumstances.
When will I know whether it worked?
The treated vein closes progressively after the procedure, so the assessment comes at follow-up rather than on the day — clinical assessment and vascular ultrasound where indicated. Symptom improvement can also be gradual rather than immediate.
Can varicose veins come back afterwards?
Incomplete closure and recurrence are both on the documented risk list, and new venous problems can develop in veins that were never treated. That is why follow-up is part of the treatment and why the clinic assesses closure rather than assuming it.
What if I have prominent surface veins as well?
They may need separate treatment: the clinic documents that mechanochemical ablation may be combined with phlebectomy when clinically appropriate. Whether both are needed, and in what order, comes out of the ultrasound assessment.
Book a Consultation at Ium Hazi Varicose Vein Clinic
If you are considering mechanochemical ablation in Seoul, the ultrasound assessment establishes whether your vein is suitable and whether a non-thermal approach is the right one for it.
To arrange a consultation, use the clinic's contact page or call . English-language support is available for international patients.
Ium Hazi Varicose Vein Clinic is on the 2nd floor of K-Tower, 320 Seocho-daero, Seocho-gu, Seoul 06633, Republic of Korea. More about the clinic is on its About Us page.
Disclaimer
Individual results may vary. All surgical and non-surgical procedures have potential risks and limitations. Your suitability for treatment, expected results, costs, and recovery time will be discussed with Dr. Dong-Hyuk Kim during your personal consultation. The information provided is for general educational purposes and does not guarantee a specific treatment outcome.
Sources & Further Reading
Other Services
Explore additional treatments offered by our specialists.
Endovenous Laser Ablation
Endovenous laser ablation is the closure of an abnormal vein from the inside using laser energy delivered along a fibre placed under ultrasound guidance, used for appropriately diagnosed venous reflux and the varicose vein symptoms that follow from it.
Learn More
Vascular Ultrasound Examination
A vascular ultrasound examination evaluates the condition of the leg veins — deep, saphenous, subcutaneous and perforating — assessing their size, shape, location and blood-flow patterns, and showing reflux in real time.
Learn More
Mechanochemical Ablation
Mechanochemical ablation closes a refluxing vein by combining two actions in one catheter pass: mechanical irritation of the inner vein wall and delivery of a chemical sclerosing agent, without heat.
Learn More